For people with inflammatory bowel disease, feeling better on treatment doesn't always mean a permanent improvement – the disease can flare again.
A study suggests part of the explanation may lie in intestinal cells that stay fragile even when symptoms such as abdominal pain and diarrhea are controlled.
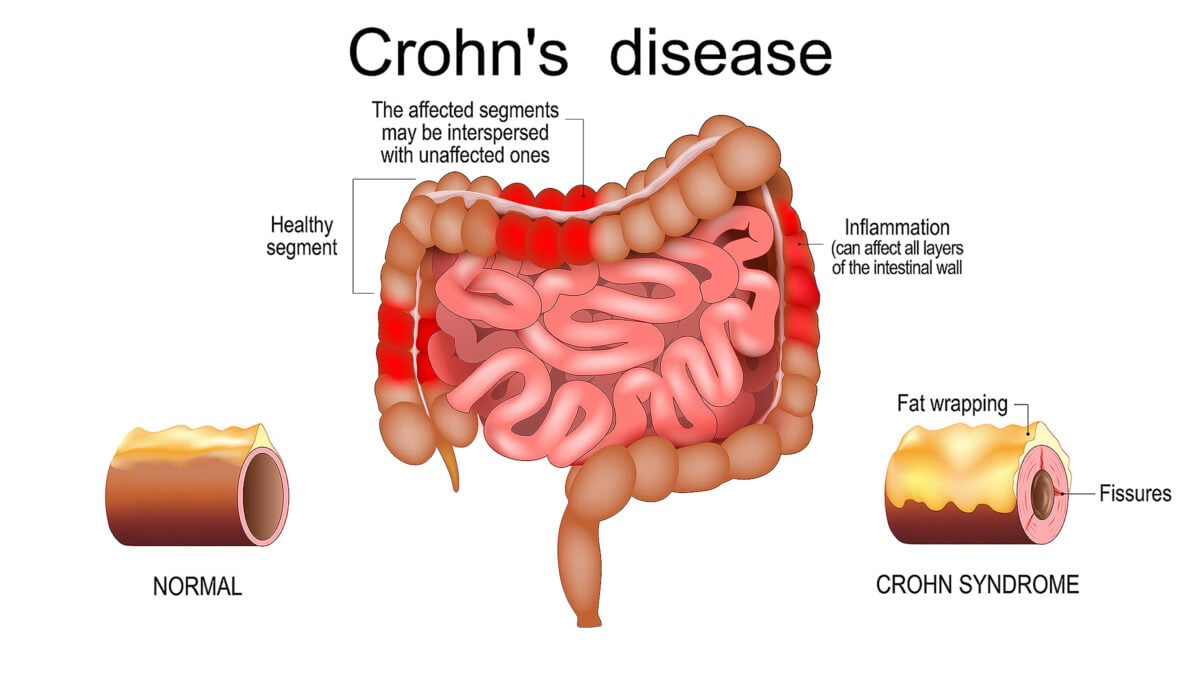
Crohn's disease and ulcerative colitis are the main forms of inflammatory bowel disease (IBD). Both involve chronic inflammation of the digestive tract.
Treatment can bring IBD into remission, a period when its activity subsides, but another flare can follow.
Researchers found signs of abnormal cell death in gut tissue even from patients whose disease was under control.
"The bowel may still carry a vulnerability that is not apparent from symptoms alone," gastroenterologist Britt Christensen, head of the Inflammatory Bowel Disease Unit at the Royal Melbourne Hospital, told ScienceAlert.
The study, published in Science, examined more than 900 intestinal biopsies, small tissue samples, from 80 people with and without IBD. Most patients with IBD had inactive or mildly active disease.
Led by researchers at Australia's Walter and Eliza Hall Institute, the team investigated the intestinal lining: a protective layer that constantly rebuilds itself.

Normally, controlled cell death removes unwanted or damaged cells, while stem cells produce replacements.
The researchers found that inflammation could change how intestinal cells behave, making them more vulnerable to abnormal death signals.
Some signals were detectable even in tissue without obvious inflammation, hinting that problems could persist beneath an apparently healthy surface.
"This suggests that clinical remission does not always mean the underlying biology has returned to normal," Christensen explained.
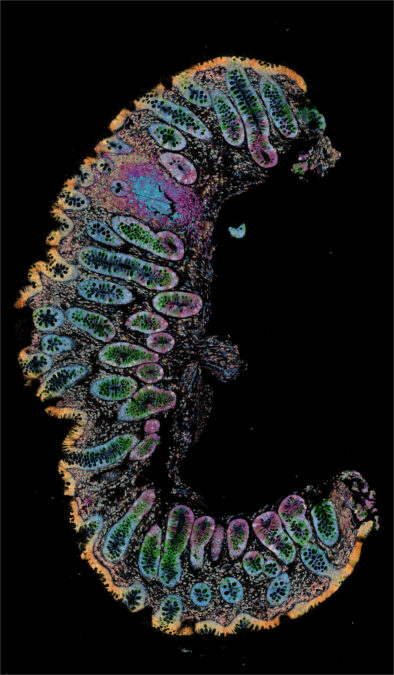
To investigate further, the researchers grew miniature intestinal tissues from human samples. These laboratory models, called organoids, let scientists examine how cells respond to inflammation. Other researchers have used human cells to recreate features of IBD on a chip.
The experiments revealed an unexpected connection between two ways cells die. Patient tissue showed signals associated with necroptosis, a process that can rupture cells and release contents that promote inflammation.
But when organoids were exposed to inflammatory signals, their cells died mainly through apoptosis, a more orderly process of cellular dismantling.
Blocking necroptosis did not prevent cell death under the conditions tested. So drugs targeting a signal seen in diseased tissue may not be enough on their own to protect cells.
In the lab, deleting specific genes protected particular cell types. Further research is needed to determine whether these mechanisms can be safely targeted in patients.
The team examined whether the tissue findings were associated with later flares.
Of 52 patients with IBD, 30 had follow-up information covering two to three years. Sixteen experienced a flare requiring intensified or changed treatment, while 14 remained stable. Twenty-two were lost to follow-up.
Those who later relapsed had elevated levels of a cell-death signaling marker compared with people without IBD. However, that comparison doesn't establish whether the marker can tell who will relapse and who won't.
Patients who relapsed also had greater microscopic inflammation initially. Larger studies could potentially establish whether the signals provide useful information beyond existing inflammation measurements.
"The follow-up findings are promising but preliminary," Christensen cautioned.

For now, the findings may help explain why the disease keeps coming back, though they aren't a test doctors can use to predict a flare.
"Protecting the lining and its ability to regenerate could therefore complement treatments that control inflammation," Christensen said.
But cell-death pathways also serve essential functions, including removing damaged or potentially cancerous cells.
"We have not shown that blocking these mechanisms safely prevents flares in patients," Christensen said.
The longer-term goal is what she calls "molecular healing": addressing the cellular problems that persist beneath apparent recovery. Whether that can keep patients well for longer is yet to be tested.
The research has been published in Science.
This article was fact-checked by Rebecca Dyer and edited by Rebecca Dyer. While we pride ourselves on our process, we are only human. If you spot a mistake, please let us know.